If you’ve been experiencing painful periods, pelvic pain, pain during sex or difficulty falling pregnant, you may have had an ultrasound to look for a possible cause.
And sometimes the result comes back as “normal”.
For many women, that can be reassuring. But if your symptoms are continuing, it can also leave you wondering: If my ultrasound is normal, does that mean I definitely don’t have endometriosis?
The short answer is no.
A normal ultrasound does not always rule out endometriosis.
What is endometriosis?
Endometriosis is a condition where tissue similar to the lining of the uterus grows outside the uterus.
It can occur in different areas of the pelvis, including around the ovaries, fallopian tubes, pelvic lining, bowel and bladder.
Endometriosis can cause inflammation, scarring and adhesions, although the way it affects each person varies considerably.
Some people have extensive endometriosis with relatively few symptoms. Others can have significant pain despite having only small or superficial areas of disease.
This is one of the reasons endometriosis can sometimes be difficult to diagnose.
What can an ultrasound detect?
A pelvic ultrasound is an important part of investigating pelvic pain and suspected endometriosis.
When performed by an experienced sonographer, particularly using transvaginal ultrasound, it can sometimes identify features associated with endometriosis.
These may include:
ovarian endometriomas, sometimes called “chocolate cysts”
deeper areas of endometriosis involving structures within the pelvis
signs that pelvic organs are not moving freely because of adhesions
other conditions that may be contributing to symptoms, such as fibroids or ovarian cysts.
For some patients, ultrasound can provide very useful information and help guide treatment or surgical planning. However, ultrasound has limitations.
Why can endometriosis be missed on ultrasound?
Not all forms of endometriosis are easy to see on imaging.
In particular, superficial endometriosis can involve small or thin areas on the surface of the pelvic lining. These changes may not be visible on a standard pelvic ultrasound.
This means it is possible to have symptoms consistent with endometriosis even when your ovaries, uterus and other pelvic structures appear normal on the scan.
The quality of the ultrasound also matters.
A routine pelvic ultrasound and an ultrasound specifically assessing for endometriosis are not always the same thing. Specialist imaging may involve a more detailed assessment of the way pelvic organs move and a closer examination of areas where deep endometriosis commonly occurs. Even with specialist imaging, however, not every case can be identified.
Does the severity of my pain tell you how much endometriosis I have?
Not necessarily.
One of the frustrating things about endometriosis is that the amount of disease seen on imaging or during surgery does not always match the severity of someone’s symptoms.
A person with relatively limited endometriosis can experience significant pain, while another person with more extensive disease may have few symptoms.
Pain can also become more complex over time.
Endometriosis may be one contributor, but pelvic floor muscle tension, bladder or bowel conditions, nerve sensitivity and other causes of pelvic pain can sometimes occur alongside it.
That is why we treat the person and their symptoms, not simply the scan result.
What symptoms might suggest endometriosis?
Endometriosis can present differently from person to person, but symptoms may include:
periods that are significantly painful or interfere with normal activities
pelvic pain at other times of the month
pain during or after sex
pain with bowel movements, particularly around your period
pain when passing urine around your period
heavy or irregular bleeding
difficulty falling pregnant
ongoing abdominal or pelvic discomfort.
Period pain that regularly causes you to miss work, school, exercise or social
activities is worth discussing with your doctor.
Severe pain should not simply be dismissed as something you have to put up with.
What happens if my ultrasound is normal but my symptoms continue?
A normal scan is one piece of information. It should not be the end of the
conversation if your symptoms are continuing to affect your quality of life.
Your doctor may talk with you about your symptoms in more detail, including when the pain occurs, whether it changes throughout your menstrual cycle and whether you have bladder, bowel or fertility concerns.
Depending on your individual circumstances, management may include pain relief, hormonal treatment, pelvic physiotherapy or further assessment.
Some people may also benefit from specialist imaging or referral to a gynaecologist with experience in endometriosis.
Historically, laparoscopy — keyhole surgery — was often considered necessary to confirm endometriosis. Today, diagnosis and treatment are increasingly based on a combination of symptoms, clinical assessment and imaging, and surgery is not automatically required for everyone.
For some patients, however, laparoscopy may still be appropriate, particularly when symptoms remain significant despite treatment, fertility is a concern, imaging suggests more complex disease or there are other reasons surgery may be beneficial.
The decision is individual.
Could something else be causing my symptoms?
Yes. Absolutely. This is another reason a thorough assessment is important.
Pelvic pain can have many possible causes, including adenomyosis, ovarian cysts, fibroids, pelvic floor dysfunction, bladder conditions and gastrointestinal disorders such as irritable bowel syndrome.
Sometimes more than one condition is contributing at the same time.
Investigating pelvic pain is therefore not simply about finding, or ruling out, endometriosis. The aim is to understand what may be driving your symptoms and find a management approach that works for you.
The important thing to remember
If your ultrasound is normal but you are still experiencing significant pelvic pain or other symptoms associated with endometriosis, your symptoms still deserve to be investigated.
A normal ultrasound can rule out some conditions and provide useful reassurance, but it cannot exclude every form of endometriosis.
You know when something does not feel right in your body.
If pain is regularly interfering with your periods, sex, work, exercise, bowel or bladder function, fertility or everyday life, speak with your GP or gynaecologist about the next step.
There are options for further assessment and treatment, and you do not need an abnormal ultrasound result before starting that conversation.
By Dr Abby Evans
By Dr Abby Evans

Nobody really tells you what sex is supposed to feel like after having a baby. There is often plenty of discussion about when it is “safe” to have sex again, but much less about whether it is comfortable, whether you feel ready, or what to do if it hurts. For many women, intimacy after birth feels different for a while. That can be due to physical healing, hormonal changes, pelvic floor changes, fatigue, breastfeeding, scar tissue, or simply the fact that your body has been through something significant. Pain should not be dismissed as something you just have to push through.
Why can sex be painful after childbirth?
There is rarely one single reason. The type of birth you had can matter, but it is not the whole story. Women who have had vaginal births may experience discomfort related to tears, episiotomy scars or pelvic floor changes. Women who have had caesarean births can also experience painful sex, including from pelvic floor tension, hormonal changes or pain around abdominal and pelvic tissues. One of the most common contributors, particularly while breastfeeding, is vaginal dryness. Breastfeeding lowers estrogen levels. This can make the vaginal tissues thinner, drier and more sensitive, which may lead to burning, stinging or pain with penetration. For some women, this settles as breastfeeding reduces and hormone levels change. Others need a little more help along the way.
Scar tissue can be sensitive
If you had a perineal tear or episiotomy, the area could remain tender even after it has technically healed. Scar tissue is less flexible than the surrounding tissue and may feel tight, sore or sensitive. Sometimes the discomfort is very localised. Other women describe a pulling or burning sensation. This does not necessarily mean anything has healed badly. But persistent scar pain is worth assessing, because there are treatments that can help. Pelvic floor physiotherapy can be particularly useful in this situation.
The pelvic floor is not always “weak”
There is a common assumption that after having a baby, pelvic floor problems always come down to weakness. That is not always the case. Some women actually develop pelvic floor muscles that are too tight or overactive. This can happen after birth trauma, tearing, prolonged labour, pain, fear of pain, or simply because the body starts guarding an area that has been uncomfortable. When the pelvic floor cannot relax properly, penetration can become painful. This is one reason pelvic floor exercises are not always the answer. If the muscles are already overactive, doing more strengthening exercises may not be helpful. A pelvic floor physiotherapist can assess whether the issue is weakness, tightness, poor coordination, scar sensitivity, or a combination of factors.
What about breastfeeding and low estrogen?
Breastfeeding-related low estrogen can cause symptoms that are very similar to menopausal vaginal dryness.
Women may notice:
- dryness
- burning
- irritation
- pain during sex
- a sensation of tightness
- increased sensitivity around the vaginal opening
Lubricants can help reduce friction during sex, and vaginal moisturisers may help with day-to-day dryness. In some cases, low-dose vaginal estrogen may also be considered. Whether that is appropriate depends on your individual circumstances and should be discussed with your OBGYN or GP.
Sometimes pain creates more pain
This is an important part of the conversation. If sex has hurt once or twice, it is completely understandable to become apprehensive about trying again. The body can start to anticipate pain. Muscles tighten. You may feel tense before anything has even happened. That tension can then make penetration more uncomfortable. This is not “all in your head”. It is a very real physical response to pain and anticipation. It is also why repeatedly trying to push through painful sex is rarely helpful. There is no prize for persevering through discomfort.
When should you seek help?
Some mild tenderness early in the postnatal period is not unusual. But if pain is persistent, significant, worsening, or stopping you from having the kind of intimacy you would like, it is worth being assessed. It is also worth seeking review if you have:
- ongoing bleeding with sex
- significant vaginal dryness or burning
- persistent scar pain
- pelvic pressure or heaviness
- urinary symptoms
- pain deep in the pelvis
- pain that is affecting your confidence or relationship
A proper assessment can help identify whether the issue is hormonal, muscular, scar-related, pelvic floor-related, or due to another gynaecological cause.
What can help?
Treatment depends very much on the cause. That might include lubricants, vaginal moisturisers, pelvic floor physiotherapy, scar massage, local vaginal estrogen in selected women, treatment of infection or skin conditions where present, or simply allowing more time for healing. Sometimes it is about adjusting expectations too. There is a lot happening after a baby arrives. Sleep deprivation, feeding, hormonal shifts, body changes, recovery from birth and the mental load of caring for a newborn all influence intimacy. There is no universal timeline for when sex should feel normal again.
The main thing I want women to know
Painful sex after having a baby is common, but that does not mean it should be ignored. There is usually a reason for it, and in many cases, there are practical things we can do to make a real difference. You do not need to wait until it becomes a major problem before bringing it up and you certainly do not need to keep having painful sex because you feel you “should” be ready by now. Your recovery deserves the same care and attention as every other part of the postnatal period.
By Dr Abby Evans
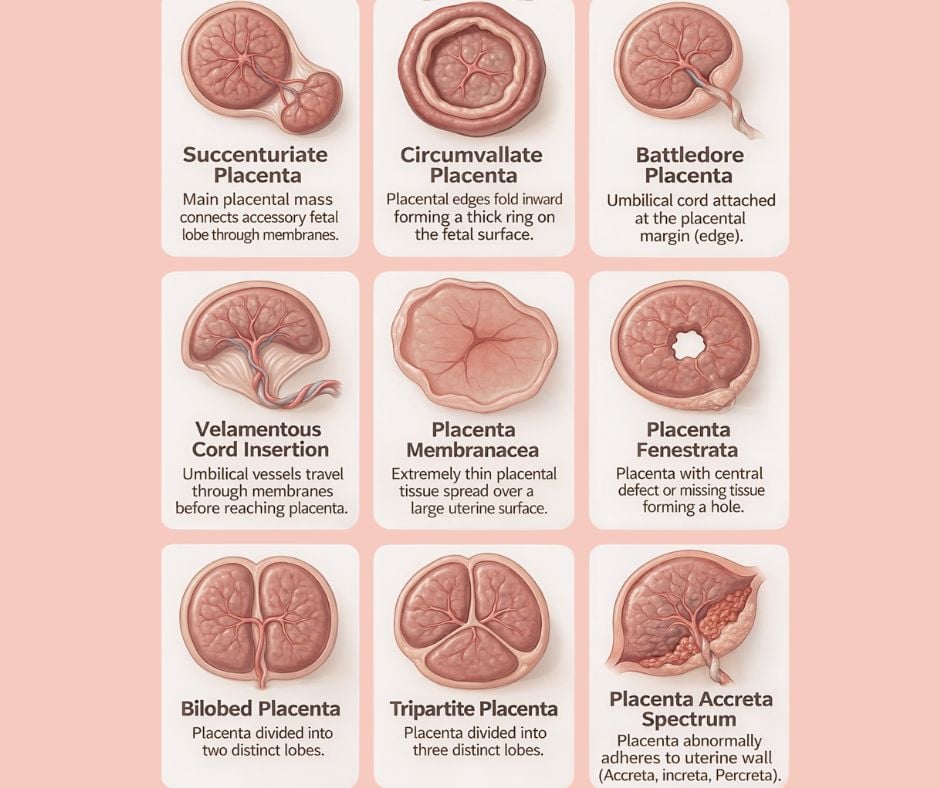
During pregnancy, the placenta is one of the most remarkable organs your body creates. It develops specifically to support your baby, delivering oxygen, nutrients and hormones while removing waste products.
Most of the time, the placenta forms in a fairly standard way. It attaches to the wall of the uterus, grows into a round disc shape, and the umbilical cord inserts somewhere near the centre. But like many things in pregnancy, there can be variations in how the placenta forms.
These differences are often picked up on ultrasound or noticed after birth when the placenta is examined.
Hearing unfamiliar terms related to the placenta can sometimes cause unnecessary anxiety, so it helps to understand what these variations actually mean.
Why placental structure can vary
The placenta develops from early pregnancy tissue and grows rapidly during the first trimester. As it expands across the uterine wall, small differences in how the tissue forms or where blood vessels travel can lead to variations in its appearance. Importantly, many of these variations are simply anatomical differences rather than medical problems.
Variations in placental lobes
Sometimes the placenta forms with more than one section, or “lobe”. A bilobed placenta means the placenta has two main sections connected by blood vessels. A tripartite placenta has three lobes instead of one. There is also a variation called a succenturiate lobe, where a small accessory lobe develops separate from the main placenta but remains connected through the membranes. Most of the time these findings do not cause complications, but knowing they are present helps guide monitoring during pregnancy and ensures that the entire placenta is delivered safely after birth.
Differences in cord attachment
Another variation relates to where the umbilical cord attaches. Normally the cord inserts near the centre of the placenta, but sometimes it attaches closer to the edge. This is called a battledore placenta. In a rarer variation known as velamentous cord insertion, the cord vessels travel through the membranes before reaching the placenta rather than being protected within the placental tissue itself. When identified on ultrasound, this can simply mean we monitor the pregnancy a little more closely to ensure blood flow to the baby remains optimal.
Variations in placental shape
Occasionally the placenta develops structural differences in its surface. A circumvallate placenta occurs when the edges of the placenta fold inward, forming a raised ring around the outer edge. Another rare variation is placenta membranacea, where placental tissue spreads thinly across a wider area of the uterus. There are also uncommon findings such as placenta fenestrata, where a small central gap appears within the placental tissue. Many of these are simply interesting anatomical findings rather than something that affects pregnancy significantly.
Placenta accreta spectrum
One placental condition that does require careful planning is placenta accreta spectrum. This occurs when the placenta attaches too deeply into the wall of the uterus. Depending on the depth of attachment, this can be classified as accreta, increta or percreta. Fortunately this is relatively uncommon, but when identified during pregnancy it allows the obstetric team to carefully plan delivery to ensure the safest outcome for both mother and baby.
Why monitoring matters
One of the reasons routine ultrasound scans are so valuable is that they allow us to identify placental position and structure during pregnancy. Most placental variations do not affect the course of pregnancy, but knowing about them helps us tailor care when necessary.
Every pregnancy is unique
The placenta is a temporary but incredibly complex organ, and no two pregnancies are exactly the same. Variations in placental shape, lobes or cord insertion are often simply part of the natural diversity of pregnancy. What matters most is careful monitoring, good communication and a care plan that supports both mother and baby throughout the pregnancy journey.
Dr Abby
Many women experience changes, discomfort, or irritation in their vulva or vagina at some point in their lives, but too often, they feel
awkward bringing it up. Whether it’s itching, burning, pain, or changes in skin texture, these symptoms are worth attention, not embarrassment.
I thought I would talk about some of the more common vulval and vaginal conditions, how
they present, and when to seek help. And I hope this helps whoever is reading this.
Vulval irritation and itching
Irritation can happen for many reasons, and not all of them are infections.
● Dermatitis or allergic reactions: Fragranced soaps, pads, or laundry detergents are
common culprits.
● Lichen sclerosus: A chronic skin condition that causes thin, white, itchy patches on
the vulva. It’s not contagious, but it does need long-term management to prevent
scarring or narrowing of the vaginal opening.
● Lichen planus: Similar to lichen sclerosus but can affect the vagina as well,
sometimes causing soreness or small erosions.
These conditions often need topical prescription creams and ongoing monitoring, not
over-the-counter antifungal treatments, a reason why you need to seek proper medical
advice.
Pain and burning
Pain or burning in the vulva or vagina isn’t “normal,” even if you’ve been told it’s just
sensitivity. Possible causes include:
● Vulvodynia: Chronic pain without an obvious cause. It can feel like burning, stinging,
or rawness, often triggered by touch, sex, or even tight clothing.
● Atrophic vaginitis: Thinning of the vaginal tissue due to low oestrogen, especially
after menopause, breastfeeding, or long-term hormonal suppression.
● Infections: While yeast infections and bacterial vaginosis are common, if treatment
isn’t working, further testing may be needed to confirm the cause.
Persistent pain deserves a proper assessment, including a gentle physical exam and
sometimes swabs or a biopsy to clarify the diagnosis.
Changes in skin, discharge, or appearance
Noticing a lump, bump, colour change, or patch of thickened skin on the vulva can be
unsettling. Most are benign (like cysts or skin tags), but occasionally, they can indicate a
precancerous or cancerous change.
Warning signs to have checked include:
● Persistent pain or itching that doesn’t settle
● Ulcers or raised patches
● Bleeding, cracking, or pigment changes in the vulval skin
● Unusual or persistent discharge
Early assessment makes a huge difference. Vulval and vaginal cancers are rare, but
catching them early leads to far better outcomes.
Why women delay seeking care
Many women hesitate to bring up these types of symptoms. Sometimes it’s embarrassment;
sometimes it’s the assumption that discomfort is “just normal” after childbirth, menopause, or
ageing. Others have been dismissed in the past or told it’s “in their head.”
But your comfort, confidence, and sexual wellbeing matter.
At SHE Medical, we aim to make these conversations straightforward, respectful, and
private. You deserve to feel comfortable in your own body and to get answers when
something doesn’t feel right.
If you’ve noticed ongoing vulval or vaginal changes, irritation, pain, itching, or anything new –
please don’t ignore it. Most conditions are manageable with the right treatment plan, and
early assessment helps rule out more serious causes.
Your body is speaking to you. We’re here to listen.
Dr Sean Holland

Itching, burning, or unusual changes in the skin of your vulva or vagina can be a symptom of vulvar or vaginal dermatoses. This common and yet uncomfortable skin condition affects many women.
Symptoms can include:
- Persistent itching or burning
- Rashes, redness, or white patches
- Pain during intercourse or urination
These signs can point to conditions like lichen sclerosus, eczema, or psoriasis. If over-the-counter treatments aren’t helping, it’s important to see a gynaecologist who specialises in these issues. We can diagnose and treat the condition properly, preventing complications and improving your comfort.
Please don’t wait, early treatment is key to managing symptoms and maintaining your vulvar health. Reach out if you’re experiencing persistent symptoms. These symptoms are not pleasant so you want to get onto it as soon a possible.

When embarking on your fertility journey, understanding all of your options can make a world of difference. Preimplantation Genetic Screening (PGS) and Preimplantation Genetic Diagnosis (PGD) are advanced techniques that can screen embryos for genetic conditions before they are implanted, helping reduce the risk of inherited disorders and improving the likelihood of a healthy pregnancy.
This testing is done by expert embryologists at QFG, and we will provide guidance, care, and the reassurance that you’re in good hands every step of the way.
At SHE medical we understand that every family’s journey is unique, and we’re here to help you navigate the complexities with compassion and expert advice. If you’re exploring IVF or considering genetic testing as part of your treatment plan, let’s talk about how we can help you create the future you’ve been dreaming of.